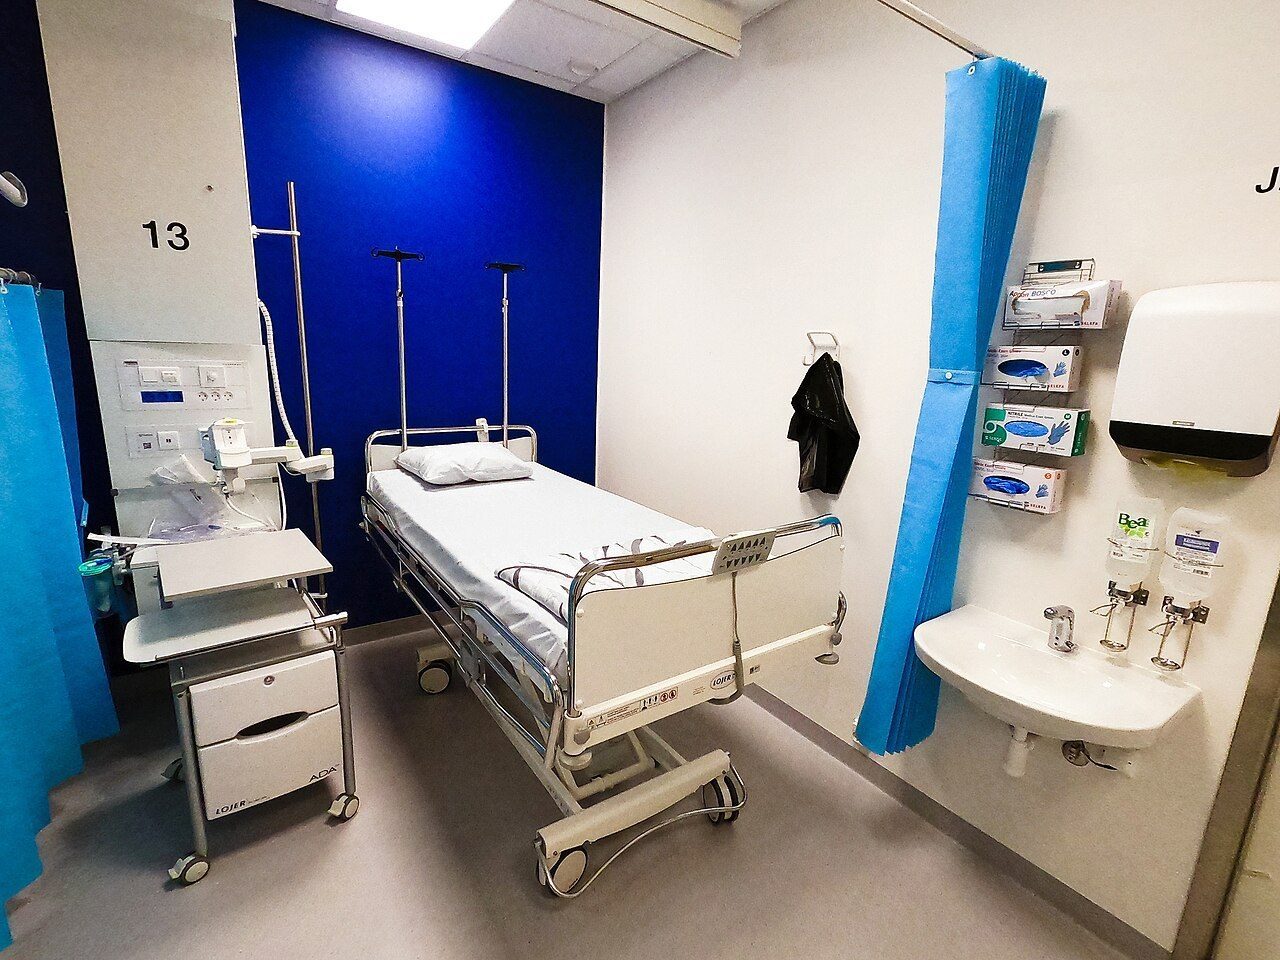
Hospitals brace for overlapping flu, COVID, and RSV demand
Hospital leaders are watching early respiratory season for overlapping flu, COVID, and RSV admissions that can tighten bed space. Staffing and pediatric beds are the usual pinch points. Households can help by using urgent care for mild illness and keeping vaccine appointments.
Hospitals enter October trying to avoid last winter's double-booking of flu, COVID, and RSV patients. Capacity planners watch emergency-department boarding, pediatric ward fills, and staff sick calls as community virus levels rise.
Mild illness still belongs at primary care, urgent care, or a nurse line in most cases. Saving emergency departments for breathing trouble, chest pain, confusion, or dehydration helps keep beds for people who need them. Parents of infants with RSV risk factors should ask clinicians early about prevention options that may be offered this season.
Vaccination remains the main community lever. Flu shots for most people, COVID updates for eligible adults, and RSV products for selected older adults and infants can blunt severe disease even when they do not stop every infection.
Hospitals also plan for isolation rooms and testing supplies. When several viruses circulate together, longer lab turnaround and stricter isolation rules can slow bed turnover. That is a systems problem patients feel as longer waits.
Households can prep now: refill chronic medicines, know the after-hours nurse number, and agree on who watches children if a parent is ill. Those small steps matter more when waiting rooms are packed.
Employers can help by expanding sick leave so mildly ill workers stay home. That reduces workplace spread that later fills emergency departments. Community mask habits during peak weeks remain a low-cost layer for crowded buses and clinics.
What we know: Hospitals are preparing for overlapping respiratory viruses as fall deepens.
What we don't: Whether this season's peak will match, beat, or fall short of last winter's strain.
Where outlets agree Hospital and public-health season briefings continue to flag overlapping flu, COVID, and RSV as the main fall capacity risk.
Where they differ Some administrators emphasize staffing shortages as the binding constraint, while others say vaccine uptake will decide how hard beds are hit.